
GIP/GLP-1 dual agonists: one peptide, two hormone receptors
A GIP/GLP-1 dual agonist is a single laboratory-made peptide that switches on the receptors for two gut hormones at once. Tirzepatide is the only one approved as a medicine so far, and it is available on prescription only. Enicepatide, VK2735 and brenipatide are still in clinical trials.
Two gut hormones behind one class
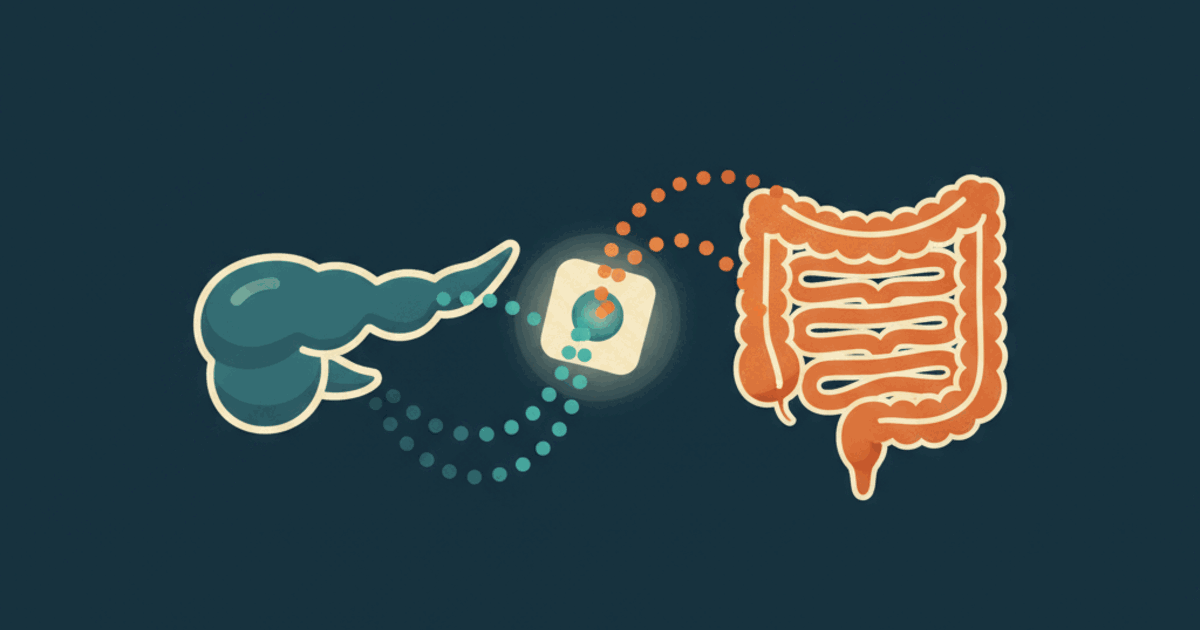
After a meal, the gut releases hormones that tell the pancreas to produce insulin. They are called incretins, and two of them are known. GIP (glucose-dependent insulinotropic polypeptide) comes from cells in the upper part of the small intestine, and GLP-1 (glucagon-like peptide-1) mostly from cells further down. Together they explain why the body releases two to three times more insulin when sugar is swallowed than when the same sugar is given straight into a vein, an observation known as the incretin effect.
The US National Library of Medicine describes GIP as a gut peptide hormone of about 43 amino acids that strongly stimulates insulin release and only weakly holds back stomach acid. That second role explains its older name, gastric inhibitory polypeptide.
Both hormones act through docking points on cells, called receptors, and a drug that switches a receptor on is called an agonist. What peptides are as a class is explained on what peptides are.
What GIP does in the body
GIP is released within minutes of eating, like GLP-1, and its best-established job is the same: it makes the insulin-producing beta cells of the pancreas release more insulin, but only while blood sugar is raised. Beyond that the two hormones part ways. According to a review in the journal Gastroenterology, GLP-1 slows the emptying of the stomach, holds back glucagon and makes people feel full, while GIP promotes energy storage through direct effects on fat tissue and also acts on bone.
The natural hormone does not last long. An enzyme in the blood called DPP-4 cuts it apart, and in a study of healthy volunteers intact GIP had a half-life of about 7.3 minutes (the time the body needs to clear half of it); in people with type 2 diabetes it was about 5.2 minutes.
One finding shaped the whole field. In a 1993 study, the strongest effect of GIP on insulin release was 54% lower in people with type 2 diabetes than in healthy people, a difference too large to put down to chance (p < 0.05). GLP-1 kept much of its effect: people with diabetes reached 71% of the rise in C-peptide, a marker of insulin release, seen in healthy volunteers, and that gap was not statistically significant. That is why the first incretin medicines targeted GLP-1 alone, and why the benefit of adding GIP back is still debated.
Where the GIP receptor sits, and why that matters
The receptor for GIP is not confined to the pancreas, and its location explains most of the open questions about the class.
- Pancreas. The receptor sits on the beta cells that make insulin, which is the basis of the incretin effect.
- Gut. GIP itself is made by so-called K cells in the upper small intestine, while GLP-1 comes from L cells further down the gut.
- Fat tissue. GIP promotes fat storage, yet in animal studies both more and less GIP receptor activity reduced fat mass under a rich diet, a paradox the field has not resolved. A 2022 study, mainly in mice, found the receptor in fat tissue chiefly on supporting cells such as pericytes and mesothelial cells rather than on the fat cells themselves.
- Brain. Cells carrying the GIP receptor were found in several appetite-regulating areas of the hypothalamus in both mouse and human tissue. Switching these cells on in mice reduced food intake.
Most of that evidence comes from animal work, and how much of it applies to people taking a dual agonist has not been settled. The developer of brenipatide points to GIP and GLP-1 receptors throughout the body, including the brain, as its reason for testing the substance outside diabetes and weight management altogether.
Dual, single and triple agonists compared
The incretin medicines fall into three groups by the number of receptors they switch on. The third possible target is the receptor for glucagon, a hormone that raises blood sugar and influences how the body uses energy.
| Group | Receptors switched on | Example | Status of the example | Half-life of the example |
|---|---|---|---|---|
| GLP-1 agonist | GLP-1 | Liraglutide | Approved, prescription only | About 13 hours |
| GLP-1 agonist | GLP-1 | Semaglutide | Approved, prescription only | About a week |
| GIP/GLP-1 dual agonist | GIP and GLP-1 | Tirzepatide | Approved, prescription only | About 5 days |
| GIP, GLP-1 and glucagon triple agonist | GIP, GLP-1 and glucagon | Retatrutide | Investigational, approved nowhere | About 6 days |
Sources: US prescribing information for liraglutide, semaglutide and tirzepatide; the phase 1b trial of retatrutide.
A dual agonist is not simply half GIP and half GLP-1. Tirzepatide's chain is built on the GIP template, and a laboratory study from the manufacturer calculated that at the levels reached in people it occupies the GIP receptor to a greater degree than the GLP-1 receptor. At the GLP-1 receptor it favours one signalling route over another, a property called biased agonism. Newer substances strike their own balance, so two dual agonists can behave differently despite sharing a class name.
Whether and why the GIP half helps, given that GIP responds poorly in type 2 diabetes, is still debated. Reviews by researchers working with the manufacturer suggest that GIP may add its effects on fat tissue and energy balance to the appetite effect of GLP-1. The manufacturer's first human study set out to test whether GIP adds anything to GLP-1, and in mice switching on the brain's GIP receptor cells did not obviously add to the effect of switching on GLP-1 receptors. No trial that separates what each half of the molecule contributes in people could be found in the sources reviewed for this page. The individual trial results are set out in the monographs for tirzepatide, semaglutide, liraglutide and retatrutide.
Half-life, peak and trough
Natural GIP and GLP-1 disappear within minutes, so a medicine built on them has to be protected. Tirzepatide carries a fatty acid chain that makes it cling to albumin, a carrier protein in the blood, and 99% of it circulates bound in that way. According to the US label, its level peaks between 8 and 72 hours after an injection (the time called Tmax), its half-life is about 5 days, and a steady level in the blood is reached after 4 weeks of treatment.
Between two injections the level in the blood rises to a peak and falls to a low point, the trough. The longer the half-life compared with the gap between injections, the smaller that swing. Early studies of the newer dual agonists report these half-lives:
- Enicepatide. A published early-phase study reported average half-lives of about 123 to 139 hours after a single injection.
- VK2735. The developer reported a half-life of about 170 to 250 hours after single injections, with the peak reached after about 75 to 90 hours.
- Brenipatide. A company poster with interim early-phase data reported average half-lives of 9.08 to 12.5 days.
Why this matters is a hypothesis, not a finding. The brenipatide poster states that a favourable peak-to-trough ratio "may" support tolerability for the stomach and bowel. An independent analysis of 32 trials of GLP-1 medicines found that long-acting ones were associated with less nausea and vomiting but more diarrhoea than short-acting ones, which is indirect evidence at best. The tirzepatide label reports that most nausea, vomiting and diarrhoea occurred in the early weeks of treatment and became less frequent over time. No trial comparing dual agonists with different half-lives head to head could be found in the sources reviewed for this page.
The substances in the class
The table lists the GIP/GLP-1 dual agonists covered by myPeptides and their status on the date of this page.
| Substance | Developer | Stage | Main areas under study | Approval |
|---|---|---|---|---|
| Tirzepatide | Eli Lilly | Approved | Type 2 diabetes, weight management and further uses | United States since 13 May 2022, European Union since September 2022, prescription only |
| Enicepatide (CT-388) | Roche | Phase 3 | Weight management, type 2 diabetes | Approved nowhere |
| VK2735 | Viking Therapeutics | Phase 3 (injection); tablet form through phase 2, phase 3 planned | Weight management | Approved nowhere |
| Brenipatide (LY3537031) | Eli Lilly | Phase 2 and phase 3 | Alcohol and opioid use disorder, depression, bipolar disorder, schizophrenia, smoking relapse, irritable bowel syndrome, asthma, COPD | Approved nowhere |
Sources: US approval record and EU register for tirzepatide; WHO INN lists 133 and 134; Roche release of 22 September 2026; Viking releases of June 2025 and July 2026; ClinicalTrials.gov registry entries.
Enicepatide and brenipatide are described as GIP and GLP-1 receptor agonists in the World Health Organization's lists of proposed international names, the official generic names for new substances. No international name for VK2735 could be found in these lists, so it is known by its development code. Roche reported on 22 September 2026 that two phase 3 trials of enicepatide in weight management were under way. Viking reported in July 2026 that both phase 3 trials of injected VK2735 were fully enrolled and that phase 3 trials of the tablet form were expected to begin in the fourth quarter of 2026. Brenipatide is unusual for the class, because all of its registered phase 2 and phase 3 trials are in addiction, psychiatric, bowel and airway conditions rather than in diabetes or weight management. No published results from its phase 2 and phase 3 trials could be found in the sources reviewed for this page by September 2026. The individual profiles are at enicepatide, VK2735 and brenipatide, and the most recent early data are discussed on the blog.
Safety of the class
The safety picture of the class so far rests on tirzepatide, the only member with a label. Stomach and bowel complaints dominate: nausea, diarrhoea, vomiting and constipation, mostly early in treatment. The label also warns about inflammation of the pancreas, gallbladder problems, kidney damage from fluid loss and low blood sugar when combined with insulin. On 29 January 2026 the British medicines regulator strengthened the warning on acute pancreatitis for the whole group of GLP-1 and dual GLP-1/GIP receptor agonists, including rare cases in which tissue died and cases that ended in death.
- Boxed warning. The US label of tirzepatide carries a framed warning about thyroid C-cell tumours seen in rats. Whether this applies to people is stated as unknown.
- Contraindication. The label rules out use in people with a personal or family history of medullary thyroid carcinoma and in people with multiple endocrine neoplasia syndrome type 2.
For the investigational substances no label exists, and what is known about their side effects comes from trial reports, several of them company releases.
Legal status and sport
Legally the class splits in two. Tirzepatide is an approved medicine and is available on prescription only in every market covered by myPeptides. Enicepatide, VK2735 and brenipatide are investigational substances: outside a registered clinical trial there is no approved product. The FDA reports that it has warned companies that sold unapproved drugs containing tirzepatide, retatrutide and other incretin substances, "falsely labeled 'for research purposes' or 'not for human consumption'". How approved peptide medicines differ from research-labelled ones is explained on peptides vs GLP-1.
In sport the dividing line is the same. Tirzepatide is not on the WADA 2026 Prohibited List, and section 6 of the 2026 Monitoring Program covers "Markers of Semaglutide and Tirzepatide", which carries no penalty. Section S4.4 of the list, metabolic modulators, names insulins and insulin-mimetics among others but names no GIP or GLP-1 receptor agonist. The unapproved dual agonists fall under section S0, which prohibits at all times any pharmacological substance that no other section of the list covers and that has no current approval by a governmental health authority for human therapeutic use, including drugs under clinical development. The wider picture is at peptides banned in sport.
Common questions
What is a GIP/GLP-1 dual agonist?
It is a single laboratory-made peptide that switches on the receptors for two gut hormones, GIP and GLP-1. Both hormones are released after a meal and prompt the pancreas to release insulin when blood sugar is high. A dual agonist is one molecule with both activities, not two drugs mixed together.
Is tirzepatide a GIP/GLP-1 dual agonist?
Yes. The US prescribing information describes tirzepatide as a GIP receptor and GLP-1 receptor agonist whose chain is based on the GIP sequence. It was the first medicine of this class to be approved, in the United States on 13 May 2022, and it is available on prescription only.
What does GIP add to GLP-1?
That is still an open question. GIP releases insulin, acts on fat tissue and, in mice, on appetite centres in the brain. In type 2 diabetes its insulin-releasing effect is much weaker than that of GLP-1. No trial that separates what each half of the molecule contributes could be found in the sources reviewed for this page.
What is the difference between a dual and a triple agonist?
A dual agonist such as tirzepatide switches on the receptors for GIP and GLP-1. A triple agonist such as retatrutide adds a third target, the receptor for glucagon, a hormone that raises blood sugar and influences how the body uses energy. Retatrutide is still in trials and approved nowhere.
Which GIP/GLP-1 dual agonists are approved?
As of September 2026 only tirzepatide. Enicepatide and VK2735 are in late-stage trials for weight management, and brenipatide is being tested mainly outside metabolic disease, for example in alcohol use disorder and depression. None of these three is approved in any market.
Are GIP/GLP-1 dual agonists banned in sport?
Tirzepatide is not on the WADA 2026 Prohibited List; markers of it sit in the penalty-free Monitoring Program. Dual agonists that no authority has approved, such as enicepatide, VK2735 and brenipatide, fall under section S0 of the list, which prohibits unapproved substances at all times.
Why is a long half-life discussed for these drugs?
The natural hormone GIP is broken down within minutes, so the medicines are built to last days. A longer half-life means blood levels rise and fall less between injections. Whether flatter levels cause fewer stomach and bowel complaints is a hypothesis, supported so far by indirect comparisons and company data rather than by direct trials.
Sources
- US National Library of Medicine (2026). Medical Subject Headings, descriptor D005749, Gastric Inhibitory Polypeptide, scope note. MeSH. https://www.ncbi.nlm.nih.gov/mesh/68005749
- Nauck MA, Meier JJ (2018). Incretin hormones: their role in health and disease. Diabetes, Obesity and Metabolism 20 Suppl 1:5-21. https://pubmed.ncbi.nlm.nih.gov/29364588/
- Baggio LL, Drucker DJ (2007). Biology of incretins: GLP-1 and GIP. Gastroenterology 132(6):2131-2157. https://pubmed.ncbi.nlm.nih.gov/17498508/
- Deacon CF, Nauck MA, Meier J, Hücking K, Holst JJ (2000). Degradation of endogenous and exogenous gastric inhibitory polypeptide in healthy and in type 2 diabetic subjects as revealed using a new assay for the intact peptide. Journal of Clinical Endocrinology and Metabolism 85(10):3575-3581. https://pubmed.ncbi.nlm.nih.gov/11061504/
- Nauck MA, Heimesaat MM, Orskov C, Holst JJ, Ebert R, Creutzfeldt W (1993). Preserved incretin activity of glucagon-like peptide 1 7-36 amide but not of synthetic human gastric inhibitory polypeptide in patients with type-2 diabetes mellitus. Journal of Clinical Investigation 91(1):301-307. https://pubmed.ncbi.nlm.nih.gov/8423228/
- Campbell JE, Beaudry JL, Svendsen B et al. (2022). GIPR is predominantly localized to nonadipocyte cell types within white adipose tissue. Diabetes 71(5):1115-1127. https://pubmed.ncbi.nlm.nih.gov/35192688/
- Adriaenssens AE, Biggs EK, Darwish T et al. (2019). Glucose-dependent insulinotropic polypeptide receptor-expressing cells in the hypothalamus regulate food intake. Cell Metabolism 30(5):987-996. https://pubmed.ncbi.nlm.nih.gov/31447324/
- Campbell JE, Müller TD, Finan B, DiMarchi RD, Tschöp MH, D'Alessio DA (2023). GIPR/GLP-1R dual agonist therapies for diabetes and weight loss: chemistry, physiology, and clinical applications. Cell Metabolism 35(9):1519-1529. https://pubmed.ncbi.nlm.nih.gov/37591245/
- Samms RJ, Coghlan MP, Sloop KW (2020). How may GIP enhance the therapeutic efficacy of GLP-1? Trends in Endocrinology and Metabolism 31(6):410-421. https://pubmed.ncbi.nlm.nih.gov/32396843/
- Willard FS, Douros JD, Gabe MB et al. (2020). Tirzepatide is an imbalanced and biased dual GIP and GLP-1 receptor agonist. JCI Insight 5(17):e140532. https://pubmed.ncbi.nlm.nih.gov/32730231/
- Coskun T, Sloop KW, Loghin C et al. (2018). LY3298176, a novel dual GIP and GLP-1 receptor agonist for the treatment of type 2 diabetes mellitus: from discovery to clinical proof of concept. Molecular Metabolism 18:3-14. https://pubmed.ncbi.nlm.nih.gov/30473097/
- Eli Lilly and Company (2026). Tirzepatide injection (type 2 diabetes and cardiovascular product), US Prescribing Information, revision 8/2026. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=d2d7da5d-ad07-4228-955f-cf7e355c8cc0
- US Food and Drug Administration (2026). Drugs@FDA, NDA 215866 (tirzepatide), original approval 13 May 2022. openFDA. https://api.fda.gov/drug/drugsfda.json?search=application_number:%22NDA215866%22
- European Commission (2026). Union Register of medicinal products for human use, tirzepatide, EU/1/22/1685. https://ec.europa.eu/health/documents/community-register/html/h1685.htm
- Novo Nordisk (2025). Semaglutide injection (type 2 diabetes product), US Prescribing Information, revision 01/2025. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=adec4fd2-6858-4c99-91d4-531f5f2a2d79
- Novo Nordisk (2025). Liraglutide injection (type 2 diabetes product), US Prescribing Information, SPL version 31. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=5a9ef4ea-c76a-4d34-a604-27c5b505f5a4
- Urva S, Coskun T, Loh MT et al. (2022). LY3437943, a novel triple GIP, GLP-1, and glucagon receptor agonist in people with type 2 diabetes: a phase 1b, multicentre, double-blind, placebo-controlled, randomised, multiple-ascending dose trial. The Lancet 400(10366):1869-1881. https://pubmed.ncbi.nlm.nih.gov/36354040/
- Bettge K, Kahle M, Abd El Aziz MS, Meier JJ, Nauck MA (2017). Occurrence of nausea, vomiting and diarrhoea reported as adverse events in clinical trials studying glucagon-like peptide-1 receptor agonists: a systematic analysis of published clinical trials. Diabetes, Obesity and Metabolism 19(3):336-347. https://pubmed.ncbi.nlm.nih.gov/27860132/
- Chakravarthy MV, Rodriguez R, Hergarden A et al. (2026). Effects of CT-388, a once-weekly signaling-biased dual GLP-1/GIP receptor agonist, on weight loss and glycemic control in preclinical models and participants with obesity. Molecular Metabolism 103:102291. https://pubmed.ncbi.nlm.nih.gov/41319798/
- Viking Therapeutics (2023). Viking Therapeutics announces results from phase 1 clinical trial of dual GLP-1/GIP receptor agonist VK2735, 28 March 2023. https://ir.vikingtherapeutics.com/2023-03-28-Viking-Therapeutics-Announces-Results-from-Phase-1-Clinical-Trial-of-Dual-GLP-1-GIP-Receptor-Agonist-VK2735
- Goldsmith P, Garhyan P, Yang S et al. (2026). Brenipatide, a GIP/GLP-1 receptor agonist: clinical data supporting dose selection for substance use, psychiatric and immunologic disorders. Poster P-175, Psych Congress 2026, New Orleans, 15-19 September 2026. Eli Lilly and Company. https://assets.ctfassets.net/mpejy6umgthp/1DBu0eLHcS9NjjpujOaamF/f0d57d38b14a73d659c3504020088e79/Brenipatide_a_GIP_GLP-1_Receptor_Agonist_DV-041369-MDD.pdf
- World Health Organization (2025). International Nonproprietary Names for Pharmaceutical Substances, Proposed INN List 133 (enicepatide). WHO Drug Information 39(2). https://cdn.who.int/media/docs/default-source/international-nonproprietary-names-(inn)/pl133.pdf
- World Health Organization (2025). International Nonproprietary Names for Pharmaceutical Substances, Proposed INN List 134 (brenipatide). WHO Drug Information 39(4). https://cdn.who.int/media/docs/default-source/international-nonproprietary-names-(inn)/pl134.pdf
- Roche (2026). Roche announces positive Phase II results for dual GLP-1/GIP receptor agonist enicepatide in people living with type 2 diabetes and overweight or obesity, media release, 22 September 2026. https://www.roche.com/media/releases/med-cor-2026-09-22
- Viking Therapeutics (2025). Viking Therapeutics announces initiation of phase 3 obesity clinical program with GLP-1/GIP agonist VK2735, 25 June 2025. https://ir.vikingtherapeutics.com/2025-06-25-Viking-Therapeutics-Announces-Initiation-of-Phase-3-Obesity-Clinical-Program-with-GLP-1-GIP-Agonist-VK2735
- Viking Therapeutics (2026). Viking Therapeutics reports second quarter 2026 financial results and provides corporate update, 29 July 2026. https://ir.vikingtherapeutics.com/2026-07-29-Viking-Therapeutics-Reports-Second-Quarter-2026-Financial-Results-and-Provides-Corporate-Update
- ClinicalTrials.gov (2026). Registry entries for brenipatide (LY3537031), including NCT07219953 (alcohol use disorder, phase 3) and NCT07412756 (major depressive disorder, phase 3). https://clinicaltrials.gov/search?intr=LY3537031
- ClinicalTrials.gov (2026). Registry entries for enicepatide, including NCT07351045 and NCT07351058 (phase 3). https://clinicaltrials.gov/search?intr=enicepatide
- Medicines and Healthcare products Regulatory Agency (2026). GLP-1 receptor agonists and dual GLP-1/GIP receptor agonists: strengthened warnings on acute pancreatitis, including necrotising and fatal cases. Drug Safety Update, 29 January 2026. https://www.gov.uk/drug-safety-update/glp-1-receptor-agonists-and-dual-glp-1-slash-gip-receptor-agonists-strengthened-warnings-on-acute-pancreatitis-including-necrotising-and-fatal-cases
- US Food and Drug Administration (2026). FDA's concerns with unapproved GLP-1 drugs used for weight loss. FDA. https://www.fda.gov/drugs/drug-alerts-and-statements/fdas-concerns-unapproved-glp-1-drugs-used-weight-loss
- World Anti-Doping Agency (2025). The 2026 Prohibited List, in force 1 January 2026, sections S0 and S4.4. WADA. https://www.wada-ama.org/sites/default/files/2025-09/2026list_en_final_clean_september_2025.pdf
- World Anti-Doping Agency (2025). The 2026 Monitoring Program, section 6. WADA. https://www.wada-ama.org/sites/default/files/2025-09/2026_list_monitoring_program_en_final_clean_september_2025.pdf
This page describes the class as it stood in September 2026. Trial programmes of investigational substances change quickly, and labels and lists are revised every year. For tirzepatide the authoritative text is the current product label in the reader's own market; questions about an individual treatment belong with a doctor or pharmacist.