
Liraglutide vs Tirzepatide: differences, evidence and safety
Answer first
Liraglutide switches on the receptor for one gut hormone, GLP-1. Tirzepatide switches on two, GIP and GLP-1. Both are approved, prescription-only medicines, liraglutide since 2009 and tirzepatide since 2022. No study comparing them directly could be found, so the trial figures below come from separate studies and cannot be ranked.
At a glance
How they work
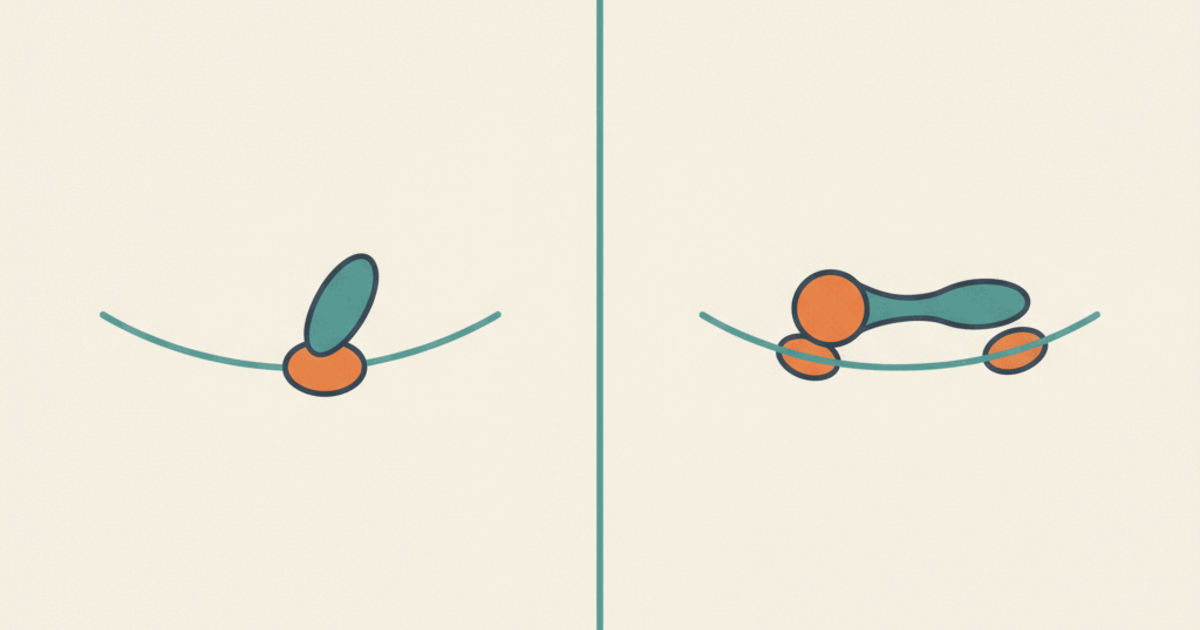
Both drugs are peptides made in the laboratory and injected under the skin [1], [2]. Both copy hormones that the gut releases after a meal. They differ in how many hormone docking points, or receptors, they switch on, and in how long they stay in the body.
Liraglutide
- One receptor, GLP-1. Liraglutide is a chain of 31 building blocks developed by Novo Nordisk. It matches the natural gut hormone GLP-1 in 97% of its sequence and switches on its receptor [1].
- Insulin only when needed. Insulin is released only while blood sugar is actually high. Glucagon, the hormone that pushes blood sugar up, is released in smaller amounts [1].
- Stomach and appetite. The stomach empties more slowly. The European product information attributes the effect on weight to appetite and fullness signals in the brain [1], [3].
Tirzepatide
- Two receptors, GIP and GLP-1. Tirzepatide is a chain of 39 amino acids developed by Eli Lilly. It copies the gut hormone GIP (glucose-dependent insulinotropic polypeptide) and also switches on the GLP-1 receptor [2].
- Stomach and appetite. Switching on the GLP-1 receptor slows the emptying of the stomach and makes people eat less [2].
- Insulin and glucagon. According to the label, the body releases more insulin and less glucagon. Both effects only come into play when blood sugar is high [2].
The GIP receptor is the core difference. How much the GIP half of tirzepatide contributes on its own is still argued over. No trial in its programme was designed to tell the two hormone systems apart [2].
The second difference is how long each lasts. Both carry a fatty acid chain that makes them cling to albumin, a carrier protein in the blood. Liraglutide's chain has 16 carbons, and the body clears half of it in about 13 hours [1]. Tirzepatide's chain has twenty carbons, and clearing half a dose takes about five days [2].
What the studies show
No study that compares liraglutide and tirzepatide directly could be found in the published record reviewed for this page.
Everything below therefore comes from separate trials. They enrolled different people, gave different doses, measured different endpoints and ran for different lengths of time. Their numbers cannot be set against each other.
Weight in adults without diabetes
Phase 3 RCT SCALE Obesity and Prediabetes randomised 3,731 adults with obesity, or with excess weight plus a related condition, and without diabetes. After 56 weeks the liraglutide group had lost 8.4 kg on average, against 2.8 kg on a dummy treatment [4].
The American labelling reports the same trial as a fall of 7.4% against 3.0%. The two sets of figures differ because missing data were filled in another way [5].
Phase 3 RCT SURMOUNT-1 allocated 2,539 adults with obesity and without diabetes at random to tirzepatide or to a dummy injection, for 72 weeks. Average weight fell by 15.0%, 19.5% and 20.9% across the three doses tested, against 3.1% on placebo [6].
Weight in adults with type 2 diabetes
Phase 3 RCT SCALE Diabetes enrolled 846 adults who also had type 2 diabetes. Over 56 weeks weight fell by 6.0% in the higher liraglutide dose arm and 4.7% in the lower one, against 2.0% on the dummy treatment [7].
Phase 3 RCT SURMOUNT-2 enrolled 938 adults who had obesity together with type 2 diabetes. By week 72 the two tirzepatide groups had lost 12.8% and 14.7% of their weight [8].
With both drugs the effect was smaller in people with diabetes than in people without it. The figures for the two groups are therefore not interchangeable [7], [8].
Keeping the weight off
Phase 3 RCT, maintenance design SCALE Maintenance took 422 adults who had already lost at least a twentieth of their weight on a low-calorie diet. Over the next 56 weeks the liraglutide group lost a further 6.2%, against 0.2% on the dummy treatment [9].
The entry rule picked people who had already responded to dieting. The American labelling therefore states that the result does not carry over to the general population [9], [5].
Phase 3 RCT, randomised withdrawal In SURMOUNT-4, all 670 participants first took tirzepatide openly for 36 weeks. Between week 36 and week 88 those who carried on lost a further 5.5%, while those switched to placebo regained 14.0% [10].
Long-term blood sugar
Both drugs were tested on glycated haemoglobin, a blood value that reflects average blood sugar over the past two to three months.
Phase 3 RCT, open-label LEAD-6 compared liraglutide with exenatide in 464 adults over 26 weeks. The value fell by 1.12 points against 0.79. Blood sugar after breakfast and after the evening meal, however, was controlled less well on liraglutide [11].
Phase 3 RCT SURPASS-1 enrolled 478 adults with type 2 diabetes who had not yet taken any diabetes medicine. After 40 weeks the value fell by 1.87 to 2.07 percentage points from a starting level of 7.9%. On placebo it crept up by 0.04 points [12].
Separate trials against a third drug
Two other drugs, semaglutide and dulaglutide, turn up in the trial programmes of both. These are separate trials with different people, lengths and designs, so they allow no direct comparison and no ranking.
- Semaglutide, for weight. In STEP 8, 338 adults without diabetes lost 6.4% on liraglutide and 15.8% on semaglutide over 68 weeks [13]. In SURMOUNT-5, 751 adults without diabetes lost 20.2% on tirzepatide and 13.7% on semaglutide over 72 weeks [14].
- Semaglutide, for blood sugar. SURPASS-2 enrolled 1,879 adults with type 2 diabetes. Their value fell by 2.01, 2.24 and 2.30 points on tirzepatide, against 1.86 on semaglutide [15].
- Dulaglutide. Tirzepatide met dulaglutide in the heart trial SURPASS-CVOT, described below [16]. Liraglutide met it in an observational study that followed people in everyday care [17].
In STEP 8, SURMOUNT-5 and SURPASS-2 everyone knew which drug they were taking, which can colour how results are judged [13], [14], [15]. The semaglutide groups were different people in each trial and cannot serve as a bridge between liraglutide and tirzepatide.
Heart
Phase 3 RCT LEADER enrolled 9,340 adults with type 2 diabetes and a high heart risk and compared liraglutide with a dummy treatment. Over a median of 3.8 years a serious heart event struck 13.0% against 14.9%, about 13% less risk (hazard ratio 0.87, range 0.78 to 0.97) [18].
Death from a heart cause occurred in 4.7% against 6.0%. Heart attacks and strokes counted separately showed no clear difference, and neither did admissions for heart failure [18].
Phase 3 RCT, active comparator SURPASS-CVOT followed 13,299 adults with type 2 diabetes and hardened arteries for a median of 210.1 weeks, roughly four years. A serious heart event occurred in 12.2% on tirzepatide and 13.1% on dulaglutide (hazard ratio 0.92, range 0.83 to 1.01) [16].
That range includes no difference at all. The trial showed that tirzepatide is no worse than dulaglutide (p = 0.003); being better was tested and not shown (p = 0.09) [16].
The designs differ in a way that matters. LEADER measured liraglutide against a dummy treatment, while SURPASS-CVOT measured tirzepatide against another active drug.
Phase 3 RCT SUMMIT followed 731 people with obesity and the stiff form of heart failure for a median of 104 weeks. Death from a heart cause or worsening heart failure, counted together, occurred in 9.9% on tirzepatide and 15.3% on placebo. The hazard ratio was 0.62, with a range of 0.41 to 0.95 [19].
Outcomes studied for only one of the two
- Liraglutide and later diabetes. The weight trial ran on to 160 weeks in 2,254 people with raised blood sugar. Type 2 diabetes was diagnosed in 2% on liraglutide against 6% on the dummy treatment. Only 1,128 reached week 160 [20].
- Liraglutide in teenagers. A trial enrolled 251 teenagers aged 12 to 17 with obesity. Over 56 weeks their body mass index score fell by 0.22 points more than on the dummy treatment. After the drug stopped, it climbed back faster [21].
- Tirzepatide and sleep apnoea. SURMOUNT-OSA enrolled 469 adults with obesity and moderate to severe obstructive sleep apnoea. By week 52 breathing interruptions fell by 20.0 and 23.8 events per hour of sleep more than on placebo [22].
- Tirzepatide and the liver. SYNERGY-NASH treated 190 adults with an inflamed, scarred fatty liver for 52 weeks. Among 157 with an assessable follow-up sample, the inflammation cleared without worse scarring in 44%, 56% and 62%, against 10% on placebo [23].
The liver result rests on a single mid-stage trial, and the larger trial meant to confirm it is still recruiting [23], [24].
Safety
No trial comparing the safety of the two drugs could be found. The figures below come from the pooled weight trials printed in each American product information. The pools enrolled different people over different periods, so the lists are not a ranking.
Liraglutide. The pooled adult weight trials covered 3,384 people on the drug and 1,941 on a dummy treatment [5].
- Stomach and bowel. Nausea affected 39.3% against 13.8%, diarrhoea 20.9% against 9.9%, constipation 19.4% against 8.5% and vomiting 15.7% against 3.9%. Complaints of this kind overall affected 68% against 39% [5].
- Pancreas and gallbladder. Sudden inflammation of the pancreas was confirmed in 9 of 3,291 people against 2 of 1,843. Gallstones occurred in 2.2% against 0.8% [5].
- A faster pulse. The resting heart rate rose by 2 to 3 beats a minute on average [5].
- Boxed warning, United States only. In rats and mice, liraglutide causes tumours of a particular thyroid cell, more often at higher amounts and longer exposure. Whether this applies to people is unknown. The European product information carries no such warning [1], [25].
- Who must not have it in the United States. Anyone who has had that type of thyroid cancer or has it in the family. The same applies to anyone with a particular inherited hormone syndrome. In Europe, allergy to the drug is the only listed bar [1], [25].
Tirzepatide. The pooled weight trials covered 3,477 people on the drug, compared with placebo [26].
- Stomach and bowel. Nausea affected 25–29% against 8%, diarrhoea 19–23% against 8%, constipation 11–17% against 5% and vomiting 8–13% against 2%. Complaints of this kind overall affected 56% against 30% [26].
- Stopping treatment. Side effects led 4.8–6.7% of participants to stop, against 3.4% on placebo [26].
- Boxed warning. In male and female rats, tirzepatide causes tumours in the C-cells of the thyroid gland, more often at higher doses and longer exposure. Whether this applies to people is unknown [2], [26].
- Who must not take it. People with medullary thyroid cancer, personally or in the family, or with the inherited condition multiple endocrine neoplasia type 2 [2], [26].
- Further label warnings. Pancreas inflammation, kidney damage from fluid loss, gallbladder trouble, low blood sugar alongside insulin and worsening diabetic eye disease [2], [26].
Points the two share. The labels of both warn about kidney damage after fluid loss and about stomach contents reaching the lungs during anaesthesia [1], [2]. Both state that a pen must never be passed between people, even with a fresh needle [1], [2].
In January 2026 the British regulator strengthened its warnings on sudden pancreas inflammation and named both substances [27].
Why this page lists no doses. Liraglutide and tirzepatide are prescription-only wherever they are approved. Choosing an amount is a matter for the product information and the prescribing doctor. This page therefore names dose levels only by their rank among those tested, never as an amount.
Legal status
Liraglutide is an approved, prescription-only medicine in all seven markets its monograph covers. Europe authorised it on 30 June 2009 and the United States on 25 January 2010. American generic versions have been approved since 23 December 2024 [25], [28], [29]. Tirzepatide is approved and prescription-only in eight markets. The United States cleared it on 13 May 2022 and the European Union on 15 September 2022 [30], [31], [32]. In sport, neither is on the 2026 prohibited list. Tirzepatide has been on the penalty-free monitoring programme since 1 January 2026; liraglutide is not in it [33], [34], [35]. The monographs reflect the position on 10 and 6 September 2026.
Used together?
The myPeptides blend directory lists no product that combines liraglutide and tirzepatide.
No study of the two drugs given together could be found in the sources reviewed for this page. Both act on the GLP-1 receptor, and tirzepatide adds the GIP receptor [1], [2]. The liraglutide labels advise against combining several products of this kind [1], [5]. Both drugs are available only on prescription.
Frequently asked questions
Which is better, liraglutide or tirzepatide?
The evidence does not say, because no trial comparing the two directly could be found. In SCALE Obesity and Prediabetes (3,731 adults without diabetes), the labelled weight fall over 56 weeks was 7.4% on liraglutide, against 3.0% on a dummy treatment. In SURMOUNT-1 (2,539 adults without diabetes), the highest tested dose of tirzepatide lowered weight by 20.9% over 72 weeks, against 3.1% on placebo. The two trials differ in people, length and method, so the figures do not rank the drugs.
Is liraglutide or tirzepatide safer?
No trial comparing their safety directly could be found. With both drugs, nausea, diarrhoea, constipation and vomiting are the most common complaints. The labels of both also warn about inflammation of the pancreas and about gallbladder trouble. The rates come from different pooled trials, so they do not rank the two.
What is the difference between liraglutide and tirzepatide?
Liraglutide switches on one hormone receptor, GLP-1. Tirzepatide switches on two, GIP and GLP-1, from a molecule built on the GIP template. The body clears half of liraglutide in about 13 hours and half a dose of tirzepatide in about five days. Both are approved prescription medicines, liraglutide in seven markets and tirzepatide in eight.
Can liraglutide and tirzepatide be taken together?
No study of the two drugs given together could be found, and the myPeptides blend directory lists no combination of them. Both act on the GLP-1 receptor, and the liraglutide labels advise against combining several products of this kind. Both are available only on prescription.
Has liraglutide ever been tested against tirzepatide?
No such trial could be found in the sources reviewed for this page. Each drug was tested against semaglutide in separate trials: liraglutide in STEP 8, tirzepatide in SURPASS-2 and SURMOUNT-5. Those trials enrolled different people, so their results cannot be chained into a ranking.
Are liraglutide and tirzepatide banned in sport?
Neither is on the 2026 prohibited list of the World Anti-Doping Agency. Tirzepatide has been on the monitoring programme since 1 January 2026, which only records how often it turns up and carries no penalty. Liraglutide is not in the monitoring programme.
How long do liraglutide and tirzepatide stay in the body?
The body clears half of liraglutide in about 13 hours and half a dose of tirzepatide in about five days. Both carry a fatty acid chain that makes them cling to albumin, a carrier protein in the blood. Liraglutide's chain has 16 carbons, tirzepatide's has twenty.
Sources
- Liraglutide injection (type 2 diabetes product) — US Prescribing Information. Novo Nordisk Inc., SPL version 31, published 17 November 2025. DailyMed setid 5a9ef4ea-c76a-4d34-a604-27c5b505f5a4. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=5a9ef4ea-c76a-4d34-a604-27c5b505f5a4
- Tirzepatide injection (type 2 diabetes and cardiovascular product) — US Prescribing Information. Eli Lilly and Company, revision 8/2026. DailyMed setid d2d7da5d-ad07-4228-955f-cf7e355c8cc0. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=d2d7da5d-ad07-4228-955f-cf7e355c8cc0
- European Medicines Agency, European public assessment report for liraglutide (weight-management product), EMEA/H/C/003780, authorised 23 March 2015, revision 19, product information file dated 31 July 2025; sections 4.1, 4.3, 4.4, 4.8 table 4 and 9. https://www.ema.europa.eu/en/medicines/human/EPAR/saxenda
- Pi-Sunyer X, Astrup A, Fujioka K et al. (2015). A randomized, controlled trial of liraglutide in weight management (SCALE Obesity and Prediabetes). New England Journal of Medicine 373(1):11-22. PMID 26132939. DOI 10.1056/NEJMoa1411892
- Liraglutide injection (weight-management product) — US Prescribing Information. Novo Nordisk Pharmaceutical Industries LP, SPL version 22, published 15 June 2026. DailyMed setid 3946d389-0926-4f77-a708-0acb8153b143. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=3946d389-0926-4f77-a708-0acb8153b143
- Jastreboff AM, Aronne LJ, Ahmad NN et al. (2022). Tirzepatide once weekly for the treatment of obesity (SURMOUNT-1). New England Journal of Medicine 387(3):205-216. PMID 35658024. DOI 10.1056/NEJMoa2206038
- Davies MJ, Bergenstal R, Bode B et al. (2015). Efficacy of liraglutide for weight loss among patients with type 2 diabetes (SCALE Diabetes). JAMA 314(7):687-699. PMID 26284720. DOI 10.1001/jama.2015.9676
- Garvey WT, Frías JP, Jastreboff AM et al. (2023). Tirzepatide once weekly for the treatment of obesity in people with type 2 diabetes (SURMOUNT-2). The Lancet 402(10402):613-626. PMID 37385275. DOI 10.1016/S0140-6736(23)01200-X
- Wadden TA, Hollander P, Klein S et al. (2013). Weight maintenance and additional weight loss with liraglutide after low-calorie-diet-induced weight loss (SCALE Maintenance). International Journal of Obesity 37(11):1443-1451. PMID 23812094. DOI 10.1038/ijo.2013.120
- Aronne LJ, Sattar N, Horn DB et al. (2024). Continued treatment with tirzepatide for maintenance of weight reduction in adults with obesity (SURMOUNT-4). JAMA 331(1):38-48. PMID 38078870. DOI 10.1001/jama.2023.24945
- Buse JB, Rosenstock J, Sesti G et al. (2009). Liraglutide once a day versus exenatide twice a day for type 2 diabetes (LEAD-6). The Lancet 374(9683):39-47. PMID 19515413. DOI 10.1016/S0140-6736(09)60659-0
- Rosenstock J, Wysham C, Frías JP et al. (2021). Efficacy and safety of a novel dual GIP and GLP-1 receptor agonist tirzepatide in patients with type 2 diabetes (SURPASS-1). The Lancet 398(10295):143-155. PMID 34186022. DOI 10.1016/S0140-6736(21)01324-6
- Rubino DM, Greenway FL, Khalid U et al. (2022). Effect of weekly subcutaneous semaglutide vs daily liraglutide on body weight in adults with overweight or obesity without diabetes (STEP 8). JAMA 327(2):138-150. PMID 35015037. DOI 10.1001/jama.2021.23619
- Aronne LJ, Horn DB, le Roux CW et al. (2025). Tirzepatide as compared with semaglutide for the treatment of obesity (SURMOUNT-5). New England Journal of Medicine 393(1):26-36. PMID 40353578. DOI 10.1056/NEJMoa2416394
- Frías JP, Davies MJ, Rosenstock J et al. (2021). Tirzepatide versus semaglutide once weekly in patients with type 2 diabetes (SURPASS-2). New England Journal of Medicine 385(6):503-515. PMID 34170647. DOI 10.1056/NEJMoa2107519
- Nicholls SJ, Pavo I, Bhatt DL et al. (2025). Cardiovascular outcomes with tirzepatide versus dulaglutide in type 2 diabetes (SURPASS-CVOT). New England Journal of Medicine 393(24):2409-2420. PMID 41406444. DOI 10.1056/NEJMoa2505928
- Giorgino F, Bhattacharya I, Sapin H et al. (2023). The real-world observational prospective study of health outcomes with dulaglutide and liraglutide in patients with type 2 diabetes (TROPHIES): final, 24-month analysis. Diabetes, Obesity and Metabolism 25(12):3690-3701. PMID 37700627. DOI 10.1111/dom.15244
- Marso SP, Daniels GH, Brown-Frandsen K et al. (2016). Liraglutide and cardiovascular outcomes in type 2 diabetes (LEADER). New England Journal of Medicine 375(4):311-322. PMID 27295427. DOI 10.1056/NEJMoa1603827
- Packer M, Zile MR, Kramer CM et al. (2025). Tirzepatide for heart failure with preserved ejection fraction and obesity (SUMMIT). New England Journal of Medicine 392(5):427-437. PMID 39555826. DOI 10.1056/NEJMoa2410027
- le Roux CW, Astrup A, Fujioka K et al. (2017). 3 years of liraglutide versus placebo for type 2 diabetes risk reduction and weight management in individuals with prediabetes: a randomised, double-blind trial. The Lancet 389(10077):1399-1409. PMID 28237263. DOI 10.1016/S0140-6736(17)30069-7
- Kelly AS, Auerbach P, Barrientos-Perez M et al. (2020). A randomized, controlled trial of liraglutide for adolescents with obesity (SCALE Teens). New England Journal of Medicine 382(22):2117-2128. PMID 32233338. DOI 10.1056/NEJMoa1916038
- Malhotra A, Grunstein RR, Fietze I et al. (2024). Tirzepatide for the treatment of obstructive sleep apnea and obesity (SURMOUNT-OSA). New England Journal of Medicine 391(13):1193-1205. PMID 38912654. DOI 10.1056/NEJMoa2404881
- Loomba R, Hartman ML, Lawitz EJ et al. (2024). Tirzepatide for metabolic dysfunction-associated steatohepatitis with liver fibrosis (SYNERGY-NASH). New England Journal of Medicine 391(4):299-310. PMID 38856224. DOI 10.1056/NEJMoa2401943
- ClinicalTrials.gov, registry query for tirzepatide; 279 registered studies as at 6 September 2026. https://clinicaltrials.gov/search?intr=tirzepatide
- European Medicines Agency, European public assessment report for liraglutide (diabetes product), EMEA/H/C/001026, authorised 30 June 2009, marketing authorisation holder Novo Nordisk A/S, ATC A10BJ02, revision 25, legal status prescription only; product information sections 4.1, 4.3, 4.4 and 9. https://www.ema.europa.eu/en/medicines/human/EPAR/victoza
- Tirzepatide injection (weight-management product) — US Prescribing Information. Eli Lilly and Company, revision 8/2026. DailyMed setid 487cd7e7-434c-4925-99fa-aa80b1cc776b. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=487cd7e7-434c-4925-99fa-aa80b1cc776b
- MHRA. GLP-1 receptor agonists and dual GLP-1/GIP receptor agonists: strengthened warnings on acute pancreatitis, including necrotising and fatal cases. Drug Safety Update, 29 January 2026; the substances named are dulaglutide, exenatide, liraglutide, semaglutide and tirzepatide. https://www.gov.uk/drug-safety-update/glp-1-receptor-agonists-and-dual-glp-1-slash-gip-receptor-agonists-strengthened-warnings-on-acute-pancreatitis-including-necrotising-and-fatal-cases
- Drugs@FDA / openFDA, NDA 022341 (liraglutide injection, diabetes application), approval and supplement history. Original approval 25 January 2010 as a new molecular entity; latest labelling supplement 14 October 2025. https://api.fda.gov/drug/drugsfda.json?search=application_number:%22NDA022341%22
- Drugs@FDA / openFDA, active-ingredient search LIRAGLUTIDE, retrieved 10 September 2026. Fourteen applications: NDA 022341, NDA 206321, BLA 208583 (fixed combination with insulin degludec, 21 November 2016) and eleven abbreviated applications, the first of them ANDA 215503 (Hikma) approved 23 December 2024. https://api.fda.gov/drug/drugsfda.json?search=products.active_ingredients.name:%22LIRAGLUTIDE%22&limit=100
- Drugs@FDA / openFDA, NDA 215866, approval and supplement history. Retrieved 6 September 2026. https://api.fda.gov/drug/drugsfda.json?search=application_number:%22NDA215866%22
- European Medicines Agency, European public assessment report for tirzepatide, authorised 15 September 2022, revision 21 of 28 August 2026. https://www.ema.europa.eu/en/medicines/human/EPAR/mounjaro
- Ministry of Health, Labour and Welfare / Pharmaceuticals and Medical Devices Agency (2024). Report on the Deliberation Results for tirzepatide subcutaneous injection (obesity application), 6 December 2024, English translation. https://www.pmda.go.jp/files/000278664.pdf
- World Anti-Doping Agency, The 2026 Prohibited List, in force 1 January 2026. Checked in full text on 10 September 2026: no hit for liraglutide, GLP-1 or glucagon; the nearest entry in class S4 covers insulins and insulin-mimetics, which liraglutide is not. Liraglutide is also absent from the 2026 monitoring programme, which names markers of semaglutide and tirzepatide only. https://www.wada-ama.org/en/prohibited-list
- World Anti-Doping Agency, Prohibited List. Retrieved 6 September 2026; tirzepatide is not listed for 2026. https://www.wada-ama.org/en/prohibited-list
- World Anti-Doping Agency, The 2026 Monitoring Program; direct retrieval returned an empty response on 6 September 2026. https://www.wada-ama.org/sites/default/files/2025-09/2026_list_monitoring_program_en_final_clean_september_2025.pdf